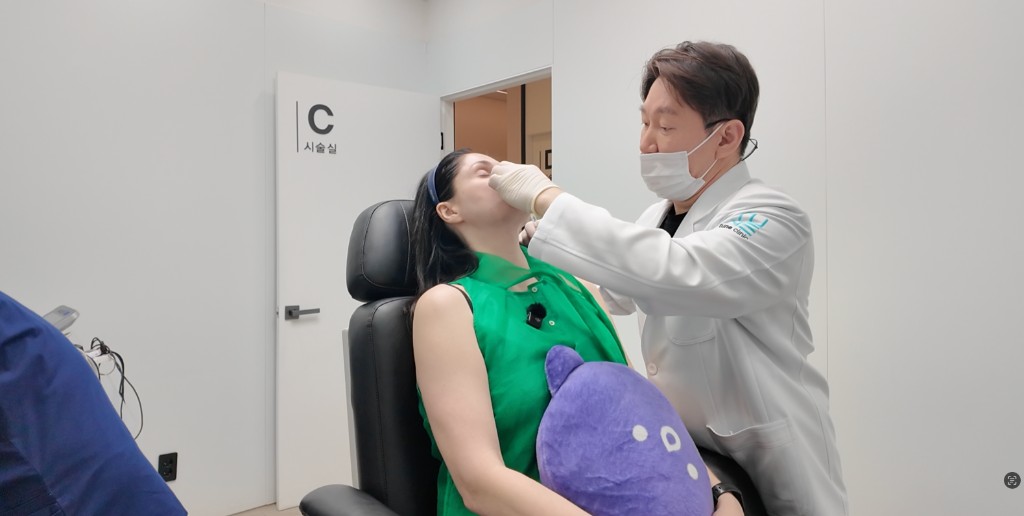
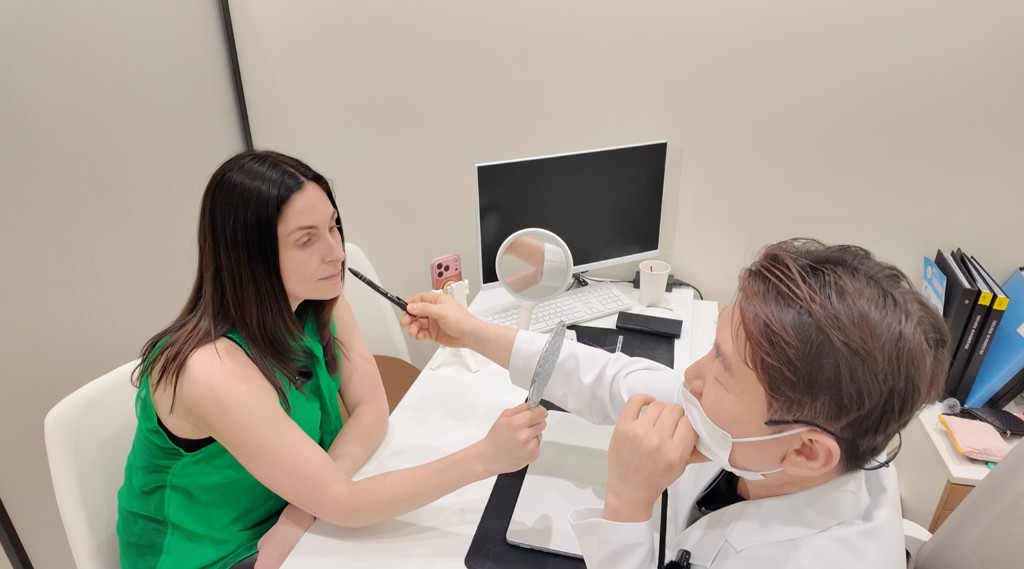
Assessment and injection technique both affect Botox outcomes. Before treatment, the clinician should review muscle movement, the intended change, previous procedures and relevant history, then explain the proposed plan and its limitations.
What Does a Physician Actually Evaluate Before Botox?
A structured pre-injection assessment covers four distinct variables. Each one independently influences where units are placed and how many are used.
1. Muscle mass and depth Facial muscles vary considerably in bulk between individuals and across the face of the same person. A heavily developed corrugator requires a meaningfully different dose than an atrophic one. Estimating this by observation alone is unreliable; experienced physicians palpate and observe dynamic contraction to form a working picture of true muscle volume.
2. Movement pattern Some patients recruit the frontalis symmetrically; many do not. One side may activate earlier, contract more forcefully, or compensate for a contralateral weakness. Injecting to a symmetry template — placing equal units at mirrored points — does not account for asymmetric recruitment and often produces asymmetric results.
3. Resting appearance The clinician should assess the area at rest as well as during movement. These findings inform the plan; they do not establish a personal duration of effect or a toxin-metabolism rate.
4. Prior treatment history Bring the product, treatment areas, dates and any previous unwanted effects if known. A previous dose should be reviewed rather than automatically repeated.
Why Injection Points Are Mapped to Vectors, Not Templates
Standard anatomical diagrams show average muscle positions. They are useful teaching tools; they are not patient-specific maps.
Individual movement patterns can affect treatment planning. The clinician should explain how the observed movement informs placement rather than relying on a universal coordinate or a millimetre rule from an article.
Marking is part of translating assessment into a treatment plan. Its duration alone is not a validated measure of the quality of that assessment.
At Tune Clinic, injection points are identified after dynamic assessment in multiple planes of movement: smiling, squinting, raising, and at rest. The marks made on the skin reflect observed vectors, not assumed ones.
Does Zone Matter for Dosing — Forehead, Glabella, Crow's Feet?
Yes, and the differences are clinically significant.
The forehead carries the frontalis, the only brow elevator. Under-dosing leaves movement unaddressed; over-dosing drops the brow. The margin between these outcomes is narrow and is determined largely by the patient's brow position at baseline and the degree of frontalis dependence for upper-lid elevation. Patients with mild ptosis or heavy brow tissue require conservative dosing here regardless of their cosmetic goals.
The glabella — the corrugator and procerus complex — generally tolerates and often requires higher unit counts relative to its surface area because the muscles involved are comparatively thick and are frequently under chronic tension. This is the zone where under-treatment is most often reported when dosing is applied uniformly across the upper face.
The crow's feet demand precision over volume. The orbicularis here is superficial and the tissue thin. Diffusion into the neighbouring zygomaticus or the lower orbicularis can alter smile dynamics in ways patients find more distressing than the original lines.
A note on the lower face
Masseter, mentalis, and platysmal dosing each introduce additional risk variables. The lower face is not a routine add-on. It requires its own assessment and should be approached with a distinct clinical logic from upper-face treatment. For patients whose primary concern involves volume loss or structural support rather than dynamic movement, filler may address what neuromodulator cannot.
How Physician-Led Assessment Changes the Outcome
The practical difference between a physician-led consultation and a protocol-driven appointment is the quality of the information that enters the dosing decision.
A protocol tells a practitioner to place a fixed number of units at fixed coordinates. A physician-led assessment tells the physician how this patient's muscles move, how deep they sit, what resting state they carry, and what history they bring into the room. The injection itself may take minutes; the assessment that makes it accurate takes longer and cannot be compressed without consequence.
This is the principle behind Tune Clinic's design method: that treatment planning precedes treatment delivery, and that the two are never reversed.
FAQ
How many units of Botox does the average person need?
There is no clinically useful average. Unit requirements depend on muscle mass, resting tension, the specific zones being treated, and the degree of movement reduction the patient wants. Published ranges exist as rough reference points, but experienced physicians calibrate from direct assessment rather than from a standard dose. Applying an average to an individual patient is one of the most common sources of unsatisfying results.
Why does Botox sometimes look uneven after treatment?
Uneven results can have several explanations, including baseline asymmetry, the treatment plan, technique and individual response. Seek assessment rather than assuming one cause from a photograph.
How long does Botox last and why does it fade faster for some people?
Duration varies with the product, area, treatment plan and individual response. Bring the date and details of previous treatment to the review instead of using a fixed expected duration to decide on reinjection.
Is Botox safe to combine with filler in the same session?
Botox and filler may be considered in one plan when they address different assessed concerns. The clinician should decide whether to combine, separate or defer them after reviewing the areas, risks and follow-up needs.
What is the difference between a consultation and a pre-treatment assessment?
A consultation is a conversation about goals, history, and options. A pre-treatment assessment is a clinical examination — dynamic observation of muscle recruitment, palpation of tissue, review of prior treatment records — that informs the specific dosing and placement decisions. Both should happen before any unit is placed. When they are compressed into the same two minutes, one of them is not being done adequately.
Ready to plan your treatment?
Tune Clinic Apgujeong offers English-language consultations with Dr. Ju and Dr. Cha — a structured assessment, not a sales call.
→ Book an appointment to pick a time that fits your Seoul itinerary.
→ Message us on WhatsApp to ask in English before you commit.